Tesamorelin vs CJC-1295: Two Ways to Stabilise GHRH
Tesamorelin keeps all 44 GHRH residues with an N-terminal cap; CJC-1295 shortens to 1-29 and substitutes four residues. How the two strategies compare.

Cover illustration: AI-generated editorial artwork. Conceptual only; not an exact molecular structure, actual laboratory result or evidence of clinical effects.
Tesamorelin and CJC-1295 solve the same problem in opposite ways. Native GHRH is destroyed within minutes, so both molecules are engineered to survive longer. Tesamorelin keeps the whole 44-residue hormone and caps its N-terminus. CJC-1295 keeps only the active 1–29 fragment, substitutes four residues, and (in the DAC version) attaches itself to albumin. The results are very different time courses.
For laboratory research use only. The research materials supplied by HealthyWelness are not approved medicines, foods or cosmetics and are not for human or veterinary use. This article summarises published research and is not medical advice.
Key points
- Same receptor: GHRH-R on pituitary somatotrophs.
- Tesamorelin: full length, chemically capped, daily administration in trials.
- CJC-1295 with DAC: shortened and substituted, half-life 5.8–8.1 days.
- Tesamorelin has phase 3 data; CJC-1295 has healthy-volunteer studies.
- No head-to-head comparison has been published.
Side-by-side
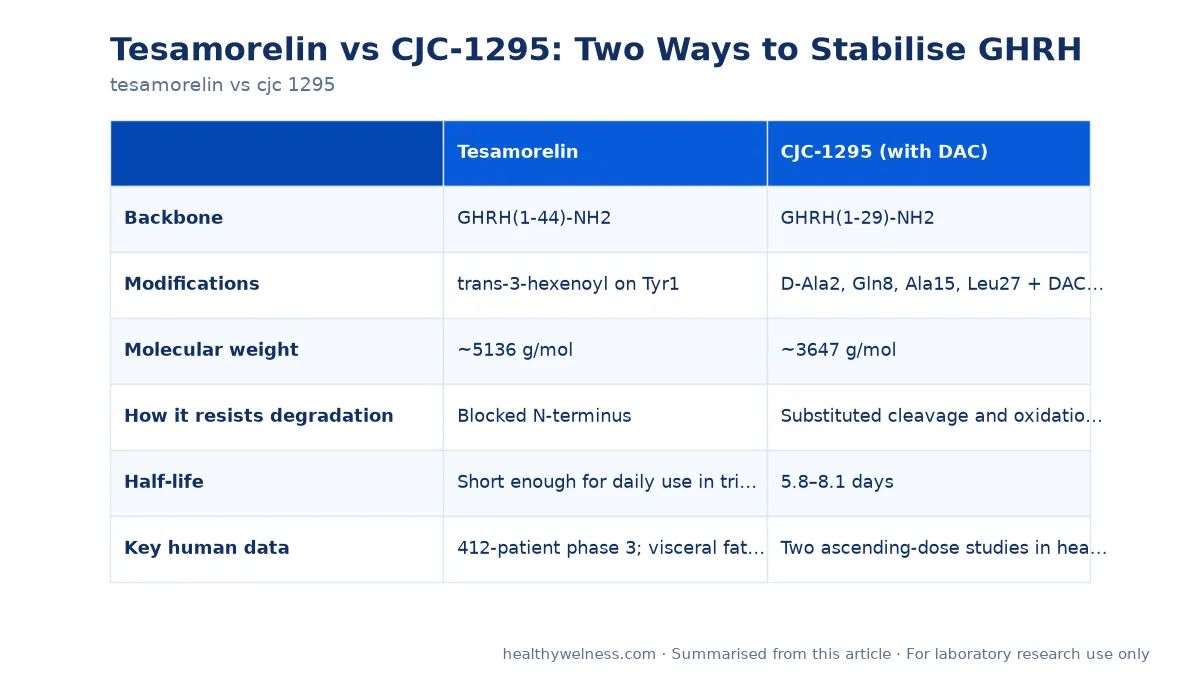
| Tesamorelin | CJC-1295 (with DAC) | |
|---|---|---|
| Backbone | GHRH(1-44)-NH2 | GHRH(1-29)-NH2 |
| Modifications | trans-3-hexenoyl on Tyr1 | D-Ala2, Gln8, Ala15, Leu27 + DAC linker |
| Molecular weight | ~5136 g/mol | ~3647 g/mol |
| How it resists degradation | Blocked N-terminus | Substituted cleavage and oxidation sites; albumin binding |
| Half-life | Short enough for daily use in trials | 5.8–8.1 days |
| Key human data | 412-patient phase 3; visceral fat −15.2%, IGF-I +81% | Two ascending-dose studies in healthy adults |
| Oxidation-prone Met27 | Present | Replaced by Leu |
Both are available for research: tesamorelin and CJC-1295 (no DAC), with a separate DAC version listed.
Two design philosophies
GHRH’s first 29 residues contain everything needed to activate the receptor, which signals mainly through cAMP (Halmos et al., 2025). From there the designers diverged.
- Tesamorelin keeps the natural sequence intact and adds a single chemical cap. The molecule the receptor sees is as close to GHRH as a stabilised analogue can be. The cost is size: at 5.1 kDa it is harder to synthesise and purify.
- CJC-1295 engineers the fragment. Four substitutions remove weak points (DPP-4 cleavage at position 2, deamidation at 8, oxidation at 27). The DAC version then adds a maleimide linker that binds albumin’s free cysteine, which is what produces the week-long half-life.
What that means for GH patterns
| Observation | Compound | Study |
|---|---|---|
| Single dose raised GH 2–10× for ≥6 days; IGF-I 1.5–3× for 9–11 days; multiple doses kept IGF-I above baseline for 28 days | CJC-1295 with DAC | Teichman et al., 2006 |
| Pulsatility preserved one week after a dose; trough GH up 7.5×, mean GH up 46%, IGF-I up 45% | CJC-1295 with DAC | Ionescu et al., 2006 |
| IGF-I +81% vs −5% placebo over 26 weeks of daily administration | Tesamorelin | Falutz et al., 2007 |
| Visceral fat reduction maintained to week 52; re-accumulated after stopping | Tesamorelin | Dhillon, 2011 |
The CJC-1295 data describe what continuous GHRH-receptor stimulation does to the GH profile; the tesamorelin data describe what months of daily stimulation do to a clinical endpoint. They answer different questions.
Practical differences in the lab
| Aspect | Tesamorelin | CJC-1295 |
|---|---|---|
| Dissolution | Larger peptide; allow extra gentle swirling | Dissolves readily |
| Oxidation risk | Met27 present; limit air and light | Met replaced; lower risk |
| Reactive group | None | DAC version has a maleimide: avoid thiol-containing buffers |
| Identity check | MS: ~5136 vs ~3647 (DAC) vs ~3368 (no DAC) g/mol — all clearly distinguishable | |
Both are covered by validated LC-MS/MS anti-doping methods, with 19 characterised in vitro metabolites across the GHRH analogue family and detection limits generally at or below 1 ng/mL (Memdouh et al., 2021).
Which to choose for an experiment
| Research aim | Better fit | Reason |
|---|---|---|
| Model GHRH signalling with a near-native ligand | Tesamorelin | Full 44-residue sequence, only the N-terminus modified |
| Study sustained receptor occupancy over days | CJC-1295 with DAC | Week-long half-life from albumin binding |
| Model short, pulse-like GHRH exposure | CJC-1295 without DAC | No albumin binder, so exposure is brief |
| Combine with a ghrelin-receptor agonist | CJC-1295 without DAC | Time course matches short-acting secretagogues |
| Compare against a compound with clinical endpoints | Tesamorelin | Phase 3 data in a defined population |
A practical point for anyone buying either: because the three CJC-1295 forms share a name, the certificate of analysis matters more here than for most peptides. Confirm from the mass whether a vial holds the DAC or the no-DAC version before planning a time course around it.
Open questions
- Does the longer tesamorelin sequence contribute to receptor binding beyond what GHRH(1-29) provides?
- Does week-long GHRH-receptor stimulation eventually desensitise the receptor?
- How do the two compare on IGF-I per unit of GH exposure?
Related research
Frequently asked questions
What is the difference between tesamorelin and CJC-1295?
Both are GHRH-receptor agonists, but they are stabilised differently. Tesamorelin is full-length GHRH(1-44) with a trans-3-hexenoyl group on the N-terminus. CJC-1295 is the shorter GHRH(1-29) with four amino acid substitutions, and the DAC version additionally binds albumin.
Which lasts longer?
CJC-1295 with DAC, by a wide margin: its estimated half-life in healthy adults was 5.8–8.1 days. Tesamorelin was given once daily in its phase 3 trials.
Which has more clinical evidence?
Tesamorelin. It has two 26-week phase 3 trials and a licensed indication. CJC-1295’s human data are two ascending-dose studies in healthy volunteers.
Do they act on the same receptor?
Yes, both activate the GHRH receptor on pituitary somatotrophs. The difference lies in structure and duration, not in target.
Can the two be compared directly?
Not from published data. No head-to-head trial exists, and the studies used different populations, durations and endpoints.
For laboratory research use only. The research materials supplied by HealthyWelness are not approved medicines, foods or cosmetics and are not for human or veterinary use. This article summarises published research and is not medical advice.
Sources
- Falutz J, et al. Metabolic effects of a growth hormone-releasing factor in patients with HIV. N Engl J Med. 2007. PMID: 18057338
- Dhillon S. Tesamorelin: a review of its use in the management of HIV-associated lipodystrophy. Drugs. 2011. PMID: 21668043
- Teichman SL, et al. Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295, a long-acting analog of GH-releasing hormone, in healthy adults. J Clin Endocrinol Metab. 2006. PMID: 16352683
- Ionescu M, et al. Pulsatile secretion of growth hormone (GH) persists during continuous stimulation by CJC-1295, a long-acting GH-releasing hormone analog. J Clin Endocrinol Metab. 2006. PMID: 17018654
- Memdouh S, et al. Advances in the detection of growth hormone releasing hormone synthetic analogs. Drug Test Anal. 2021. PMID: 34665524
- Halmos G, et al. Growth hormone-releasing hormone receptor (GHRH-R) and its signaling. Rev Endocr Metab Disord. 2025. PMID: 39934495