Sermorelin vs Ipamorelin vs Tesamorelin: Three Routes to GH
Sermorelin, tesamorelin and CJC-1295 act on the GHRH receptor; ipamorelin and MK-677 on the ghrelin receptor. How the two classes differ and compare.

Cover illustration: AI-generated editorial artwork. Conceptual only; not an exact molecular structure, actual laboratory result or evidence of clinical effects.
Research peptides that raise growth hormone fall into two families with different receptors. GHRH analogues (sermorelin, tesamorelin, CJC-1295) act on the GHRH receptor. Growth hormone secretagogues (ipamorelin, GHRP-2, GHRP-6, and the small molecule MK-677) act on the ghrelin receptor. Comparisons only make sense once that split is clear, because the two families differ in signalling, in how they shape GH pulses, and in how much evidence exists.
For laboratory research use only. The research materials supplied by HealthyWelness are not approved medicines, foods or cosmetics and are not for human or veterinary use. This article summarises published research and is not medical advice.
Key points
- GHRH receptor family: sermorelin (1-29), tesamorelin (1-44, capped), CJC-1295 (1-29, substituted; DAC version albumin-bound).
- Ghrelin receptor family: ipamorelin (pentapeptide), MK-677 (oral small molecule).
- Tesamorelin has the strongest clinical dataset; ipamorelin has the cleanest selectivity profile.
- No head-to-head trial compares them, so cross-study numbers cannot be ranked.
- Blends pair one from each family to engage both routes.
The two families side by side
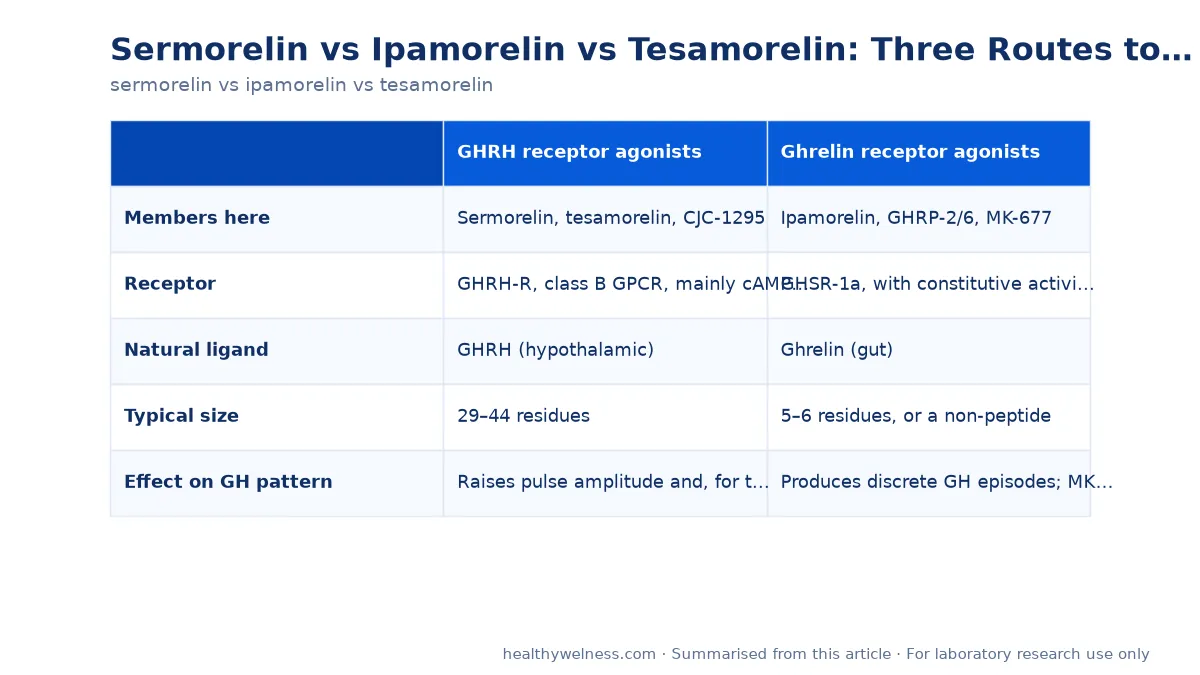
| GHRH receptor agonists | Ghrelin receptor agonists | |
|---|---|---|
| Members here | Sermorelin, tesamorelin, CJC-1295 | Ipamorelin, GHRP-2/6, MK-677 |
| Receptor | GHRH-R, class B GPCR, mainly cAMP signalling | GHSR-1a, with constitutive activity modulated by ghrelin and LEAP2 |
| Natural ligand | GHRH (hypothalamic) | Ghrelin (gut) |
| Typical size | 29–44 residues | 5–6 residues, or a non-peptide |
| Effect on GH pattern | Raises pulse amplitude and, for the DAC form, trough levels | Produces discrete GH episodes; MK-677 enhanced existing pulses |
The receptor difference is not cosmetic. GHRH-R signalling is well described as a cAMP-driven pathway in somatotrophs (Halmos et al., 2025), while GHSR is unusual in having basal activity that two opposing endogenous ligands tune up or down (Cornejo et al., 2021). That is why antagonist experiments can separate the families cleanly: in the original ipamorelin work, GHRH antagonists did not block ipamorelin’s effect (Raun et al., 1998).
The individual compounds
| Compound | Structure | Human evidence | Duration |
|---|---|---|---|
| Sermorelin | GHRH(1-29)-NH2, unmodified | Paediatric GH deficiency trials; three daily administrations in one 6-month study | Short |
| Tesamorelin | GHRH(1-44) with trans-3-hexenoyl cap | Phase 3: visceral fat −15.2% vs +5.0% placebo at 26 weeks; IGF-I +81% | Once daily in trials |
| CJC-1295 with DAC | GHRH(1-29), four substitutions + albumin binder | GH 2–10× for ≥6 days; IGF-I 1.5–3× for 9–11 days; t1/2 5.8–8.1 days | Days |
| CJC-1295 no DAC | Same core, no albumin binder | Limited published human PK | Short |
| Ipamorelin | Aib-His-D-2-Nal-D-Phe-Lys-NH2 | Phase 1 PK/PD: t1/2 ~2 h; single GH episode peaking ~0.67 h | Hours |
| MK-677 | Non-peptide, 624.8 g/mol | 25 mg/day for 2 weeks raised mean 24-h GH 97%; IGF-I into the young-adult range | Oral, once daily |
Profiles: tesamorelin, ipamorelin, CJC-1295. Sermorelin is available as sermorelin acetate.
Why blends pair one from each family
Because the receptors are distinct, a GHRH analogue and a secretagogue can be studied together to see whether combined stimulation differs from either alone. The common pairings are CJC-1295 (no DAC) with ipamorelin, and sermorelin with ipamorelin. We are not aware of peer-reviewed trials of these specific blends; the rationale rests on the separate receptor literature rather than on combination data. See CJC-1295 + ipamorelin and GH peptide blends.
MK-677: the non-peptide in the group
MK-677 (ibutamoren) is included here because it appears in the same comparisons, but it is a small molecule, not a peptide. In 32 healthy adults aged 64–81, 25 mg daily for two weeks raised mean 24-hour GH by 97% and brought IGF-I into the young-adult range. The increase came from enhancement of existing pulsatile secretion: pulse height and interpulse nadir rose without a change in pulse number (Chapman et al., 1996). A later two-year trial in 65 healthy older adults reported increased fat-free mass versus placebo, with no significant difference in total fat mass (Nass et al., 2008). Being orally active and non-peptide, it needs none of the handling precautions the peptides do.
Choosing for an experiment
| Research aim | Suitable tool |
|---|---|
| Isolate GHRH-receptor signalling | Sermorelin or tesamorelin |
| Model sustained GHRH-receptor stimulation | CJC-1295 with DAC |
| Isolate ghrelin-receptor signalling without ACTH/cortisol confounding | Ipamorelin |
| Compare peptide vs non-peptide secretagogue | Ipamorelin and MK-677 |
| Examine combined pathway stimulation | A GHRH analogue plus a secretagogue |
Whatever the design, measure GH frequently enough to catch short episodes, and remember IGF-I integrates exposure over days rather than reflecting a single GH peak.
Handling
- All the peptides: lyophilized powder at −20 °C; solutions at 2–8 °C, dark; avoid repeated freeze–thaw.
- Sermorelin and tesamorelin contain Met27 and are oxidation-sensitive; CJC-1295 replaces it with leucine.
- Concentrations: peptide reconstitution calculator; method in how to reconstitute peptides.
Open questions
- Would a head-to-head trial confirm the differences suggested by separate studies?
- Does combined GHRH-R and GHSR stimulation give additive, synergistic or redundant GH responses?
- How does prolonged stimulation of either receptor affect its responsiveness over weeks?
Related research
Frequently asked questions
What is the difference between sermorelin, ipamorelin and tesamorelin?
Sermorelin and tesamorelin are GHRH analogues acting on the GHRH receptor; ipamorelin is a pentapeptide acting on the ghrelin receptor (GHSR). Sermorelin is the unmodified GHRH(1-29) fragment, tesamorelin is full-length GHRH(1-44) with a protective N-terminal group.
Which of them has the most clinical data?
Tesamorelin, which has phase 3 trials and a licensed indication. Sermorelin’s trials date mainly from the 1980s and 1990s; ipamorelin’s human data are early pharmacokinetic studies.
Is CJC-1295 with ipamorelin different from tesamorelin?
Yes. The blend pairs a GHRH-receptor agonist with a ghrelin-receptor agonist, so two pathways are engaged. Tesamorelin engages only the GHRH receptor, but does so with a molecule that is closer to the natural hormone and better characterised clinically.
How does MK-677 fit in?
MK-677 (ibutamoren) is an orally active small molecule, not a peptide, that acts on the same ghrelin receptor as ipamorelin. In older adults it raised GH and IGF-I by enhancing existing pulsatile secretion.
Can these be ranked from weakest to strongest?
No, because they are measured in different studies with different endpoints and no head-to-head trial exists. Comparing them meaningfully requires matching the receptor, the readout and the time course.
For laboratory research use only. The research materials supplied by HealthyWelness are not approved medicines, foods or cosmetics and are not for human or veterinary use. This article summarises published research and is not medical advice.
Sources
- Raun K, et al. Ipamorelin, the first selective growth hormone secretagogue. Eur J Endocrinol. 1998. PMID: 9849822
- Gobburu JV, et al. Pharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers. Pharm Res. 1999. PMID: 10496658
- Falutz J, et al. Metabolic effects of a growth hormone-releasing factor in patients with HIV. N Engl J Med. 2007. PMID: 18057338
- Neyzi O, et al. Growth response to growth hormone-releasing hormone(1-29)-NH2 compared with growth hormone. Acta Paediatr Suppl. 1993. PMID: 8329826
- Teichman SL, et al. Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295, a long-acting analog of GH-releasing hormone, in healthy adults. J Clin Endocrinol Metab. 2006. PMID: 16352683
- Chapman IM, et al. Stimulation of the growth hormone (GH)-insulin-like growth factor I axis by daily oral administration of a GH secretogogue (MK-677) in healthy elderly subjects. J Clin Endocrinol Metab. 1996. PMID: 8954023
- Cornejo MP, et al. The ups and downs of growth hormone secretagogue receptor signaling. FEBS J. 2021. PMID: 33460513
- Halmos G, et al. Growth hormone-releasing hormone receptor (GHRH-R) and its signaling. Rev Endocr Metab Disord. 2025. PMID: 39934495